Coronary Artery Calcium Scoring in Intermediate-Risk Asymptomatic Adults
A calcium scan resolves risk in patients caught between guidelines.
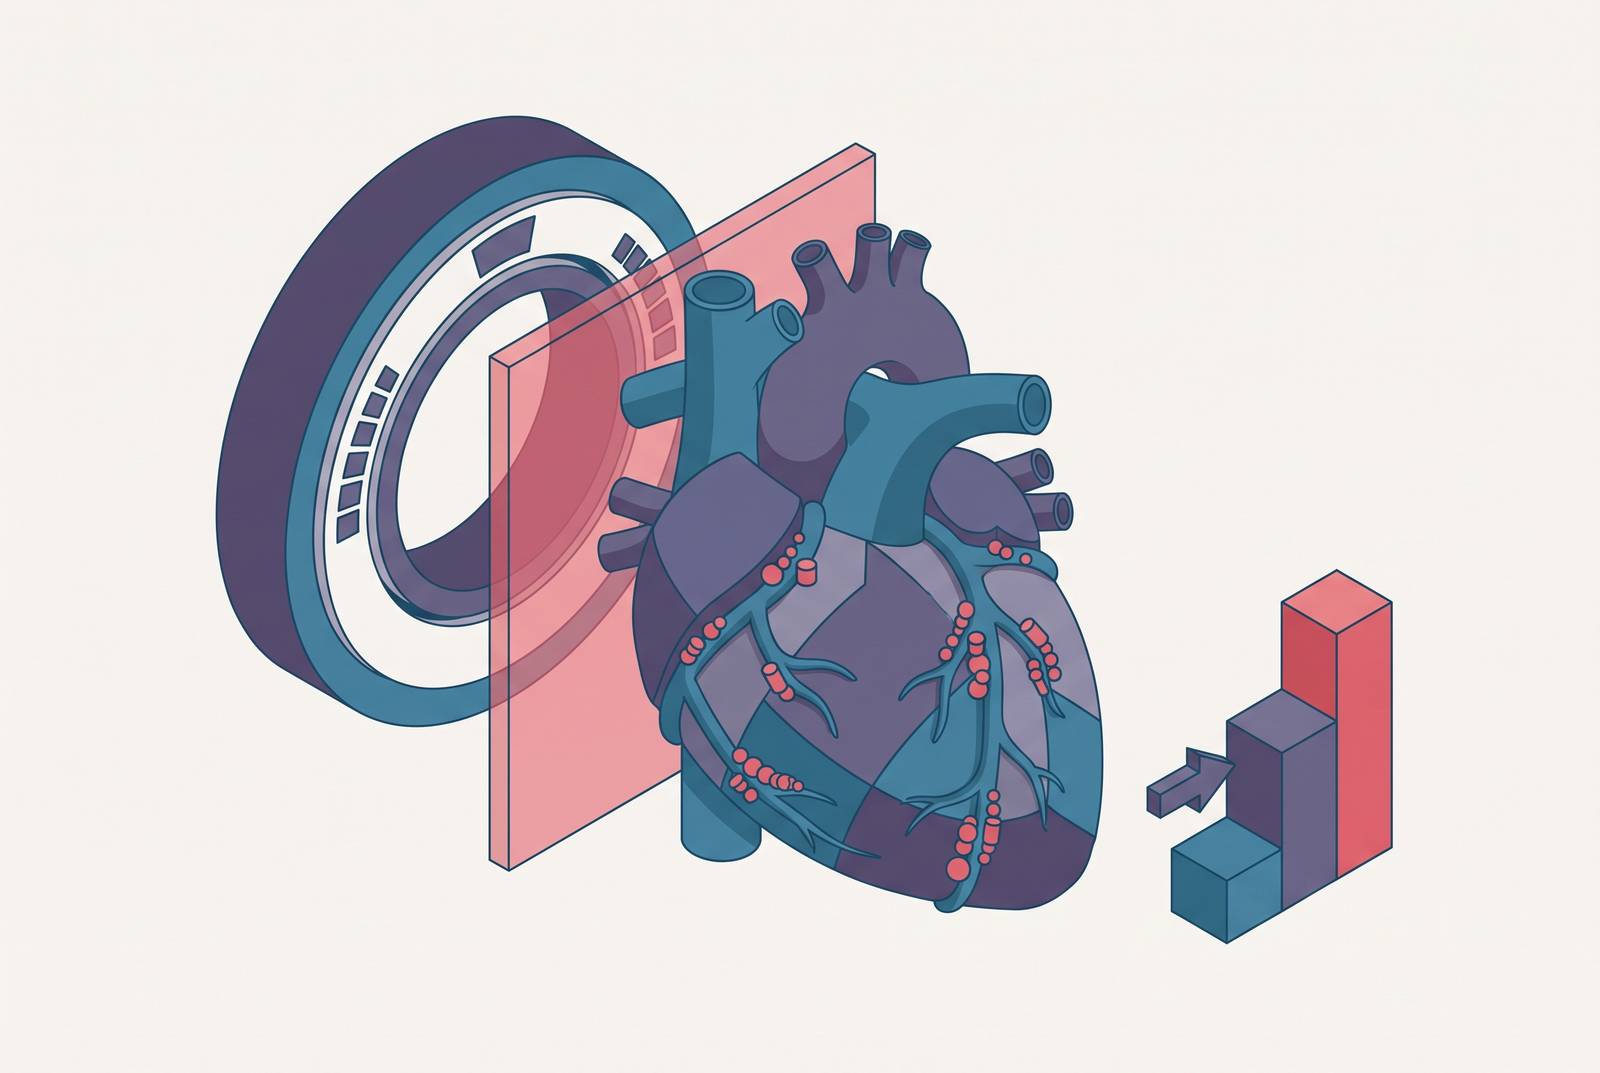
Coronary artery calcium scoring exists to answer a question that pooled cohort equations cannot: does this particular patient actually have atherosclerosis, or does the calculator just think they might? The intermediate-risk band, roughly a 7.5 to 20 percent ten-year risk by standard calculators, is where this gap matters most, because two people can land on the exact same score while carrying entirely different amounts of disease in their arteries. A risk calculator works by averaging outcomes across a population and assigning that average to an individual based on a handful of inputs: age, blood pressure, cholesterol, smoking status. It cannot tell a clinician whether plaque has actually started to build in this patient's coronary arteries. A 2025 narrative review frames the shortfall precisely: among borderline and intermediate-risk patients, pooled cohort equations leave a real prognostic gap, and CAC carries additive prognostic value that supports ordering a downstream test. The clinician facing an intermediate score is deciding on a statin, and sometimes aspirin, based on probability rather than on any direct evidence of disease, and that produces errors in both directions: some patients without a trace of plaque get treated anyway, while others who already carry a meaningful burden of calcified or soft plaque get left undertreated because their risk-factor profile looked unremarkable on paper.
What CAC scoring measures and why that matters for the intermediate problem
Coronary artery calcium scoring breaks this tie because it measures what has already happened in the artery wall, not what might happen down the line. Calcified deposits in the coronary arteries form as a direct, physical consequence of atherosclerosis, and the score built from those deposits integrates decades of metabolic and inflammatory exposure into one number. A traditional risk model looks at indirect inputs, like cholesterol and blood pressure, and infers that disease is present. CAC scoring instead reads the result those inputs produced in the artery itself. The test itself is simple to deliver: a non-contrast cardiac CT, no intravenous line, no contrast dye, with radiation exposure similar to a screening mammogram. Patients typically undergo it once, and if they score zero, repeat scanning is usually pushed off for several years rather than scheduled right away. The output is reported in Agatston units, the field's standard metric, and the guideline thresholds are 0, 1 to 99, and 100 or above, alongside an age, sex, and ethnicity percentile ranking in which the 75th percentile functions as its own separate trigger for treatment regardless of the absolute Agatston number.
How guidelines translate CAC thresholds into treatment decisions
Current ACC/AHA guidance turns these thresholds into an actual decision path, and that is what makes CAC useful rather than merely informative. A patient scoring zero can generally have statin therapy withheld or deferred, with three named exceptions where the zero result carries less weight: cigarette smokers, people with diabetes, and those with a strong family history of premature atherosclerotic cardiovascular disease. If a score falls between 1 and 99 Agatston units, the decision tips toward starting a statin, particularly if the patient is 55 or older. A score of 100 or above, or a result at or above the 75th percentile for age, sex, and ethnicity, indicates statin therapy. In the 2026 dyslipidemia guidelines, the ACC/AHA assigned CAC-guided decision-making a Class I recommendation, the highest level of endorsement the guideline language offers, and that gave this logic substantially more weight. The guideline also backs a "warranty period" for a zero score: a negative result does not need to be rechecked right away, and rescanning is only suggested after several years have passed. International guideline bodies do not all apply these thresholds identically, a divergence this article returns to once the evidence behind the thresholds has been laid out.
The evidence that CAC reclassifies intermediate-risk patients
The thresholds matter only if crossing them actually corresponds to a different observed rate of heart disease, and several independent cohorts confirm that it does. Data from the Framingham Heart Study showed that CAC reclassified the large majority of patients originally placed at intermediate ten-year coronary heart disease risk by Framingham factors alone. Among those reclassified down to low risk (172 patients), no events occurred during follow-up. Among those reclassified up to high risk (53 patients), the observed event rate matched that higher category, so the reclassification reflected something real, not statistical noise. Elias-Smale and colleagues built on this by deriving empirical CAC thresholds specifically for intermediate-risk patients, setting 50 Agatston units as the floor for reclassification down to low risk and 615 units as the threshold for reclassification up to high risk, a scheme that reassigned roughly half of all intermediate-risk individuals in the study to a more accurate category. A systematic review published in Cureus/PMC in May 2026, drawing on eight prospective cohort studies spanning 2000 to 2025, found a consistent, graded relationship between CAC and incident coronary events that held independent of conventional risk factors, with net reclassification improvement values near 0.25 among intermediate-risk patients. That review also found CAC more predictive of coronary events than of stroke, reinforcing that the test is a coronary-specific marker rather than a general cardiovascular risk gauge. The Multi-Ethnic Study of Atherosclerosis, MESA, stands as the anchor cohort behind most of this evidence, demonstrating that CAC predicts ten-year cardiovascular events and improves reclassification beyond traditional risk scores across diverse ethnic groups. A MESA sub-study following 6,751 adults, including 881 with diabetes, over eleven years found that people with diabetes and a CAC score of zero had very low rates of coronary heart disease events even when their diabetes had lasted a long time or their calculated risk score was high. Those with a CAC score of 400 or above, by contrast, had event rates more than five times higher. Diabetes is often treated as a uniform high-risk category by default, and this finding shows CAC can resolve meaningful differences in risk even within that group.
The particular value of a zero score
Reclassification runs in two directions, and the downward direction deserves attention on its own terms. A CAC score of zero is among the most reliable short-to-intermediate-term predictors of very low coronary event risk in primary prevention, but doctors still underuse it as grounds for holding off on statin therapy. The MESA data make the case concretely: even among patients with diabetes and a high calculated risk score, a zero CAC result corresponded to very low observed rates of coronary heart disease over eleven years of follow-up. The warranty period concept formalizes what a zero score should mean in practice: it does not require a repeat scan right away, and the negative result holds for a defined stretch of time rather than demanding continuous re-evaluation. None of this amounts to an argument against statins broadly. It is an argument for precision, identifying the specific patients for whom waiting is medically defensible, distinct from recommending against treatment as a general matter. The guideline's named exceptions, smokers, people with diabetes, and those with a strong family history of premature disease, are not arbitrary carve-outs. They mark the populations where noncalcified or early-stage plaque is more biologically likely to be present at a given age. That is why the reassurance of a zero score carries less force for them.
Noncalcified plaque as a residual risk when the zero-score guarantee breaks down
The clearest limit on this entire argument comes from 2026 data: plaque without calcium can carry its own independent risk of major adverse cardiac events, a risk a CAC scan is not built to detect. An analysis of quantitative plaque data from a clinical trial, presented at a cardiovascular imaging society meeting in 2026, examined thousands of patients and found that MACE rates were similar for those with noncalcified plaque regardless of their CAC status. Rates dropped markedly only for patients with neither CAC nor any detectable plaque. Zero-CAC patients who had noncalcified plaque were nearly six times more likely to have a major adverse cardiac event than zero-CAC patients without it, a hazard ratio of 5.93. A case report in JACC: Case Reports in 2026 illustrates the same mechanism in a single patient: a 48-year-old man with a CAC score of zero was followed with serial AI-assisted coronary CT angiography from 2015 to 2026 and showed progressive accumulation of noncalcified plaque over that decade, confirming that a zero score does not rule out active, evolving atherosclerotic disease. The biology behind this is straightforward: younger plaque tends to stay lipid-rich and uncalcified rather than hardening into the calcium deposits a CAC scan detects, and that pattern is most common in exactly the younger intermediate-risk patients for whom a zero score is most often invoked as reassurance. Statin therapy complicates the picture further: it can increase calcium density within existing plaque even as it stabilizes that plaque, so a rising CAC score on a treated patient does not mean what a rising score means in someone untreated. None of this makes the zero-score finding wrong. It means the reassurance is strongest in older patients, where calcified plaque tends to predominate, and weaker in younger patients, where age and other risk features deserve more weight before a clinician treats a zero score as the final word.
The evidentiary objection: what the strongest critics argue
The sharpest challenge to CAC-guided management does not dispute that the test predicts events. It argues that no randomized controlled trial has shown that acting on a CAC result actually reduces cardiovascular events. James Stein, at the University of Wisconsin, made this case directly in a published commentary opposing the ACC/AHA's Class I designation: he wrote that no RCT has proven a CAC-driven strategy reduces downstream cardiovascular disease events. His concern is structural: cohort data showing CAC predicts outcomes is not the same evidence as a trial showing that changing treatment based on CAC improves those outcomes, and folding the former into a Class I guideline recommendation risks treating prediction as if it were proof of benefit. A national preventive services panel in the U.S. has grounded a version of the same objection institutionally: it concluded that CAC produces only small gains in discrimination and reclassification, and that evidence remains inadequate to show that managing patients based on CAC scoring improves their outcomes. The gap is genuine: closing it would require randomizing thousands of intermediate-risk patients to CAC-guided care versus standard care and following them for actual cardiovascular events, a trial that has not been completed. Michael Blaha, at Johns Hopkins, offers the strongest answer available to proponents, arguing that the USPSTF critique conflates population-wide screening with targeted risk assessment. CAC, in his framing, is a tiebreaker for the specific clinical moment when a physician is already uncertain and a result could plausibly change what they prescribe, and evaluated against that narrower claim, the evidence holds up better. A systematic review in BMJ Open, published in July 2025, lands on an honest middle position: prospective data robustly support CAC's prognostic value, while RCT evidence that acting on it improves outcomes remains limited.
Why the field is moving toward CAC
Three developments across 2025 and 2026 are pushing clinical practice toward CAC even as the randomized trial gap stays open, and each rests on a practical case, not a purely evidentiary one. The 2025 AHA Scientific Statement expanded CAC's reach when it endorsed opportunistic detection on routine chest CT scans alongside AI-based scoring tools, and this could remove the biggest access barrier to the test, because it pulls a CAC score out of imaging a patient was already getting for an unrelated reason, at close to no added cost or radiation. That potential should not be overstated. The same 2025 review notes that these AI scoring tools still need validation under real-world conditions before they can be trusted at scale, so the opportunistic-detection model is a promising direction rather than a finished solution. A cost argument reinforces the shift as well: an analysis by Dr. Khurram Nasir, of Houston Methodist, found that coronary CT angiography costs substantially more than CAC scoring per patient identified who will go on to have a cardiovascular event, a material difference for clinicians weighing which anatomic imaging test to order. Set against the opportunistic-detection model, the equity implications are direct: if a CAC score can be pulled from a scan a patient already received for another reason, access to that information stops depending on whether the patient's insurance covers a dedicated cardiac scan or whether they can pay for one out of pocket.
The structural barriers that limit who benefits from CAC
The gains described above remain unevenly distributed in practice. A dedicated CAC scan is not free, and coverage for it varies by insurer and by region, so the patients most likely to get one tend to already have reliable access to primary care and the means to pay an out-of-pocket fee where insurance does not cover it. That pattern works against the patients the test is theoretically best positioned to help: people with intermediate risk scores who lack a longstanding relationship with a physician willing to order the scan and explain what the result means. Opportunistic, AI-derived scoring from scans ordered for unrelated reasons offers a real path around this barrier, but it depends on health systems actually building the infrastructure to extract and report a CAC value from routine chest imaging; the 2025 AHA statement says that work is underway at several large systems but is not yet a uniform standard. Until that kind of extraction becomes routine across most imaging centers, the benefit of CAC scoring will concentrate among patients who already have the access, the insurance, and the physician relationship needed to get a dedicated scan ordered.
Sources
- Coronary Artery Calcium Scoring for Risk Reclassification and Prediction of Hard Cardiovascular Events in Asymptomatic Adults at
- Coronary Artery Calcium Scoring for Risk Reclassification and Prediction of Hard Cardiovascular Events in Asymptomatic Adults at Low-to-Intermediate Cardiovascular Risk: A Systematic Review - PMC
- Beyond Traditional Risk Calculators: The Expanding Role of Coronary Artery Calcium Scoring in Preventive Cardiology
- Coronary atherosclerosis screening in asymptomatic adults using coronary artery calcium for cardiovascular prevention: a systematic review of randomised controlled trials and prospective cohorts
- Review began 04/21/2026 Review ended 05/12/2026 Published 05/22/2026
- Coronary Calcium Scoring in Diabetes: Recalibrating Cardiovascular Risk in 2025
- Understanding the 2026 Dyslipidemia Guidelines: CAC Scoring, Risk Enhancers, & Incidental CAC
- Coronary Artery Calcium Scoring for Risk Reclassification and Prediction of Hard Cardiovascular Events in Asymptomatic Adults at Low-to-Intermediate Cardiovascular Risk: A Systematic Review