AI Risk Stratification Models for Early Chronic Disease Detection
Machine learning models catch chronic disease by tracking patient trajectories over time.
Chronic disease does not announce itself. Kidney disease, cardiovascular disease, and diabetes all share a defining trait: they progress quietly, often for years, before a patient ever reports a symptom worth a clinic visit. Yet the tools built to catch them early are, almost without exception, designed around a single encounter: one blood draw, one blood pressure cuff reading, one set of labs plugged into a formula that spits out a percentage. This piece sets out to unpack the mismatch between how disease actually behaves and how risk gets measured.
Cardiovascular risk calculators are the clearest illustration. They rely on a handful of static measurements taken at one point in time, and the literature has documented calibration issues along with inconsistent performance once you move across different patient populations. The American Heart Association tried to close that gap in 2023 with its PREVENT equations, a genuine step forward that folded in kidney function and social determinants of health alongside the usual cardiovascular inputs. That was a genuine step forward. But even PREVENT is still a snapshot, a single frame pulled from a biological process that unfolds over a decade or more.
Consider the patient whose ApoB looks unremarkable today but has been climbing steadily for ten years. A static calculator sees only today's number, and today's number is normal, so the patient walks out labeled low-risk. The trajectory never enters the equation, and that is what actually matters. That is not a flaw in any particular formula so much as a structural property of tools built for single-visit assessment rather than for tracking something that moves.
Chronic kidney disease makes the stakes concrete. Roughly 800 million people are affected by CKD globally, and detection at that scale depends on sensitivity that binary, single-visit classification simply was not built to deliver. Late clinical detection remains common, in part because the biomarkers that would flag early disease are not the ones most clinics routinely order. None of this reflects a gap in clinical skill. It reflects a gap in architecture, and closing it requires something other than a better formula.
What AI does differently: data modalities and model architectures
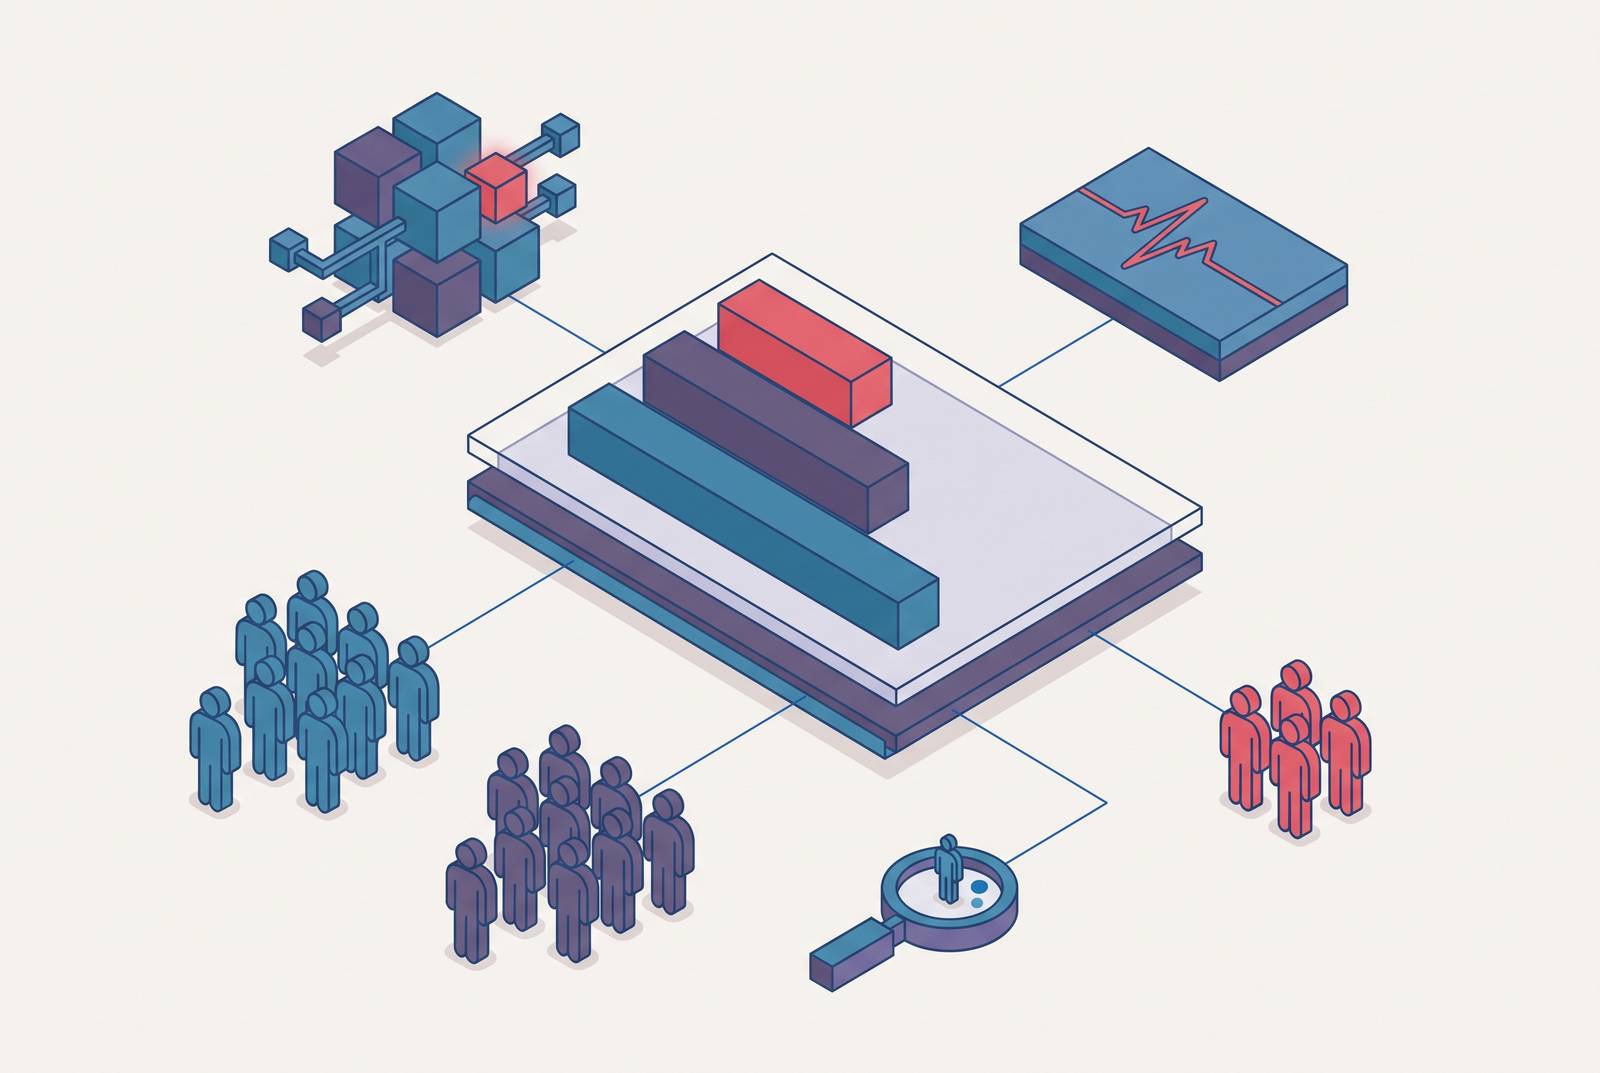
AI risk stratification does not compete with static calculators on their own terms. It changes what counts as evidence in the first place, integrating longitudinal, high-dimensional, multimodal data streams simultaneously rather than compressing a patient into a handful of numbers at one moment. That is the core distinction to understand before getting into architecture.
Four data streams dominate the current literature. Electronic health records supply longitudinal structured data, and foundation models pretrained on large EHR corpora have already shown utility across a range of clinical tasks. Social determinants of health and genetic markers widen the aperture beyond biomarkers alone, capturing signal that a lab panel never could. Medical imaging, spanning X-rays, CT, MRI, and retinal photographs, lets AI catch early signs of diabetic retinopathy, cardiovascular disease, and cancer, though imaging pipelines remain resource-intensive and stay out of reach for a lot of underserved populations.
The modeling choices layered on top of that data matter just as much as the data itself. Tree-based models like XGBoost fit structured EHR data well and carry a real interpretability advantage over deep learning. Deep learning and transformer architectures, by contrast, are built to capture temporal patterns across long EHR sequences, and a 2026 framework proposed specifically an explainable transformer architecture for early chronic disease prediction from longitudinal records. Hybrid models blend structured data with time-series health measurements to sharpen prediction further, and foundation models, pretrained broadly and then adapted to a specific clinical task, round out the toolkit.
What ties all of this together is the longitudinal advantage. Instead of comparing one value to a threshold, these models track trajectories: a lipid slope climbing over years, kidney function declining gradually, patterns that only become visible when you have more than one data point to compare. Some implementations go further still, synthesizing polygenic risk scores and coronary artery calcium quantification alongside conventional clinical calculators, a combination no single-visit tool could ever operationalize on its own. Wearables and IoMT rely on continuous biometric streams (blood glucose, heart rate, sleep patterns) captured through architectures that combine near-patient edge computing with cloud-based population analytics.
What the performance evidence shows across disease areas
Cardiovascular disease in type 2 diabetes is the most heavily studied application, and the results there are genuinely instructive. In a 2025 study, six machine learning algorithms were tested for CVD prediction in patients with T2DM, and XGBoost came out on top with a validation AUC of 0.72, moderate discriminatory power, but clinically meaningful stratification in a population where risk factors overlap and compound. Comparable models across the diabetic CVD literature tend to cluster in the 0.70 to 0.80 AUC range.
The strongest evidence in the entire body of research comes from the Kailuan cohort, a 2025 study covering 16,378 patients. This is the clearest head-to-head evidence: longitudinal AI modeling vs. static calculator, on a large real-world cohort.
Not every headline figure deserves the same confidence. A hybrid model combining structured and time-series data, tested on 1,000 diabetes patients, reported accuracy of 98.7% and an AUC of 0.99. Those numbers are eye-catching, and they warrant scrutiny precisely because they are eye-catching: a sample of 1,000, evaluated internally, is a controlled setting, not a clinical population, and figures that clean rarely survive contact with messier, more diverse cohorts.
Beyond CVD and diabetes, other disease areas are moving at different speeds. A registered clinical trial, NCT07441759, is currently developing and validating an AI model for early thrombotic risk in patients at high risk for atrial fibrillation, with major adverse cardiac events as the primary outcome, explicitly aiming to beat the CHA₂DS₂-VASc score by folding in both classical and emerging clinical factors. Results are still pending. In CKD, a 2026 hierarchical AI framework built by Alhaifi and colleagues uses only routinely collected laboratory profiles to generate continuous risk scores for patients who do not yet have a confirmed CKD diagnosis, enabling targeted follow-up before the disease progresses further, and it includes a built-in explainability layer. A retrospective study applied both machine learning and deep learning algorithms to predict five-year mortality risk in hospitalized CKD patients, with the aim of surfacing modifiable risk factors that could inform clinical decisions and resource allocation.
Those figures deserve the same caution applied above: small datasets, class imbalance, curated benchmarks, and simulation-based testing all inflate performance relative to what a model achieves once it meets a genuinely diverse patient population. Gestational conditions, preeclampsia and gestational diabetes among them, round out the picture. Current clinical risk scores and oral glucose tolerance testing show limited sensitivity, and machine learning offers a real improvement in early prediction, though the evidence base here is considerably less mature than what exists for cardiovascular disease.
Taken together, the honest picture is a spectrum. Some disease-area models show clear, quantified superiority over conventional tools on large real-world cohorts. Others look promising in controlled settings and still need multicenter validation before anyone should treat their numbers as settled. Diabetes-oriented IoMT implementations commonly report accuracy in the 95%–96% range using explainable or ensemble deep learning, while some cardiovascular frameworks report above 99% in controlled settings, according to a Frontiers in Medical Technology review.
AI models compared to traditional statistical tools and to clinicians
A 2025 narrative review mapped comparative evidence from 2019 through 2025 across classical statistical models, tree-based methods, deep neural networks, and foundation model backbones, with the specific goal of identifying when switching model classes actually improves probability accuracy and clinical net benefit over a logistic regression baseline. The consistent finding across that body of work is that machine learning methods capture intricate clinical patterns that conventional statistical models routinely miss, and a 2026 review went so far as to describe ML as increasingly indispensable for medical data analysis.
The comparison against human clinicians is where the evidence gets more provocative. Narrative review evidence from January 2026 indicates that AI diagnostic models outperformed human clinicians specifically in distinguishing among inflammatory, autoimmune, metabolic, and neurological diseases that present with overlapping symptoms. That is a narrow but meaningful claim: it is not that AI beats doctors broadly, but that it beats them at a task doctors find genuinely hard, disentangling conditions that look alike on the surface.
The Kailuan cohort result belongs here as well as in the previous section, because it is the strongest head-to-head example available anywhere in this evidence base: a C-index of 0.80 against China-PAR and other established calculators, on 16,378 real patients, is not a marginal win.
None of this should be read without qualification. Most comparisons in the literature still rely on single-center or otherwise controlled datasets, and external validity remains the persistent, unresolved gap. A study found that fewer than 2% of FDA-cleared AI and machine learning devices were backed by randomized clinical trials. Performance on a curated benchmark, however impressive, is not the same claim as performance across the range of patients a real health system actually serves.
Why explainability determines whether better predictions change clinical behavior
Deep learning models have historically operated as black boxes, and research on the 2026 explainable transformer architecture identified that lack of transparency directly as a factor limiting clinical adoption. This matters more than it might first appear. A model can post a strong AUC and still fail in practice if the clinician receiving its output has no way to understand why it flagged a given patient.
A September 2025 review framed explainable AI, XAI, as critical to integrating AI into clinical decision support, not an optional add-on but a structural requirement. One specific technique bears mentioning: model-agnostic feature attribution, the SHAP-style approach, produces higher actionability and better trust calibration than saliency maps, provided the attribution itself stays stable across similar cases. That is a concrete design choice, not an abstraction, and it carries real clinical consequences for whether a physician acts on a model's output or quietly ignores it.
That design decision addresses transparency head-on rather than leaving it for a later patch. Clinician trust and adoption, according to a review, depend not just on raw accuracy but on transparency, on clinician endorsement, and on genuinely user-centered design.
A model that beats logistic regression on paper but cannot explain its reasoning to the clinician who has to act on it is less useful, in practice, than a slightly less accurate model that can be explained and trusted. That is part of why XGBoost, with its interpretability advantage over deep learning in structured EHR settings, dominates so much of the CVD-in-T2DM literature. Accuracy alone was never going to be the whole story.
Bias and population gaps that undermine the promise of early detection
External validity remains the field's persistent, unresolved weakness. Most published models are trained and validated on cohorts that are narrow, whether by geography, by demographics, or simply by being drawn from a single hospital system. A June 2026 review in the World Journal of Nephrology named equity and calibration explicitly as the gaps standing between methodological innovation and routine clinical deployment.
The CVD literature is direct about what comes next: expanding into multicenter cohorts with genuinely diverse patient populations is framed as the necessary step, because models trained on narrow populations risk simply encoding the biases already present in that data. Imaging-based AI carries its own version of this problem. It remains resource-intensive and largely inaccessible for underserved populations, which makes scalability a structural equity issue rather than a purely technical one.
There is a genuine upside buried in this same evidence, and it deserves equal weight rather than a passing mention. Machine learning and deep learning could meaningfully increase CVD screening rates among diabetic patients and expand access to care in resource-limited communities. But that upside is conditional. It depends entirely on whether equity gaps in model design get addressed before deployment, not after. Bias and equity problems in this field are solvable; whether deployment infrastructure and regulatory oversight keep pace with the science is the open question.
The move of AI risk stratification from research into clinical practice
Real-world deployment is no longer theoretical, though it is still early. A 2025 to 2026 observational study in China enrolled eight primary healthcare institutions, four AI-enabled and four matched controls, collecting data from March 2025 through December 2025, one of the few genuine head-to-head comparisons of AI-augmented chronic disease care against standard practice. Separately, the ADEN Platform pilot, registered as NCT07727915, is a 90-day prospective study validating a clinical intelligence platform for early chronic disease risk stratification across five priority public health profiles in Colombia, notable in particular because it is running in a low-resource-country setting rather than a well-funded academic medical center.
AI's role in these deployments breaks down into distinct, separable functions rather than one monolithic capability: risk stratification, follow-up prioritization, medication management, complication prediction, and clinical decision support all appear as separate use cases in the literature. IoMT and AI-enhanced remote patient monitoring are increasingly described as mainstream for chronic conditions, with digital services handling a substantial share of patient needs, though the precise scale of that shift should be treated qualitatively rather than pinned to any single figure.
Regulation is where the picture gets uncomfortable. Regulatory clearance is, by this measure, running well ahead of the clinical evidence standards that would normally justify it. That gap is structural: devices are reaching clinicians before the evidence base that ought to support their use has caught up. Interoperability and EHR integration compound the problem further. Deploying multimodal AI at scale is not solely a data science challenge; it is a health systems infrastructure challenge, and one that occurs at every hospital trying to connect a new model to legacy records.
|Evaluating AI risk tools: clinician and health system considerations before adoption
Given all of this, a health system evaluating an AI risk stratification tool should ask a short list of questions before anything else. Was the model validated on a population that resembles the one it will actually serve, or only on a narrow cohort from somewhere else? Does it run on routinely available data, or does it demand specialized biomarkers few clinics can order on a regular basis, the way the CKD framework built on standard labs manages to do? Can its output be explained to the clinician who has to act on it, or does it arrive as an unexplained number? Has it been tested prospectively, in a real clinical setting, or only against a curated benchmark, the same gap that leaves so many FDA-cleared devices without trial-level evidence behind them? And has it been checked for calibration and bias across the demographic subgroups it will actually encounter?
These questions are not a checklist for its own sake. They are the dividing line between a research-grade model that performs beautifully in a paper and a deployable clinical tool that performs reliably in a crowded primary care clinic. The tools that clear that bar tend to share a few traits: they integrate multimodal, longitudinal data rather than a single snapshot, they produce outputs a clinician can actually interpret and act on, and they carry validation evidence from populations that look like the ones they are meant to serve. Trials like NCT07441759 for atrial fibrillation and the ADEN platform's NCT07727915 represent the frontier of that validation effort right now.
Sources
- A Risk-Oriented and Explainable Hierarchical AI Framework for Chronic Kidney Disease Classification - PMC
- Artificial intelligence in chronic kidney disease: Early detection, risk prediction, and personalized treatment strategies
- "ADEN Platform: Pilot Clinical Validation for Chronic Disease Risk Stratification in Colombia"
- throMboembolic Risk Associated To High atrIal Fibrillation riSk
- Prediction of Five‐Year Mortality Risk of Chronic Kidney Disease Using Artificial Intelligence‐Based Models: A Retrospective Study - PMC
- Frontiers | Machine learning-based coronary heart disease diagnosis model for type 2 diabetes patients
- Explainable AI in Clinical Decision Support Systems: A Meta-Analysis of Methods, Applications, and Usability Challenges - PMC
- AI and Imaging for Early Disease Risk Prediction